
Bluegrasscard
Standard Membership
-
Joined
-
Last visited
Everything posted by Bluegrasscard
-
I am going by the statistic of 40,000 for each 1% of unemployment with 5% being the wildly optimistic low number. So, 200,000 is the low estimate of excess-mortality due to economic factors of the situation. My point these are now committed and will get worse if we go into a 30s style depression. If we go another 5% (around 14%) total UE then we are looking at 400,000. Trading a medical-driven death for an economic-driven death is probably not a good discussion and this is not just a numbers discussion. Its comparing a path of increased medical risks to a path that has definite consequences that could alter the makeup of society and its entire structure well into the next few decades.
-
This doctor describes some practical "vigilance" and other reasonable actions to do. This is based on real world - not articles about studies that "may" show this or that.
-
Vigilance of individual cases when they emerge is the primary action. The brain trusts and so called leaders of the nation and state have had 4 months to figure this out. When the agendas are stripped away they had best know what is needed to manage this - if they want to. Can not offer a silver or gold bullet. But "cower in place" must come to an end sooner rather than later. The current tactics will lead to hundreds of thousands of deaths. And destroying our children's future due to over-reactive fear is just not acceptable. IMHO.
-
Friday April 17th update for UK Healthcare - still 10 inpatients related to COVID. Congratulations Kentucky - the curve was not only flattened. It never got out of the starting blocks. Now...#BackToWorkKY
-
Use of chloriquine and hydrochloriquine in fighting corona viruses IS NOT NEW. They know it after the first SARS breakout. 2005 Chloroquine is a potent inhibitor of SARS coronavirus infection and spread [h=3]Conclusion[/h]Chloroquine is effective in preventing the spread of SARS CoV in cell culture. Favorable inhibition of virus spread was observed when the cells were either treated with chloroquine prior to or after SARS CoV infection. In addition, the indirect immunofluorescence assay described herein represents a simple and rapid method for screening SARS-CoV antiviral compounds. 2012 - MERS discussion https://aac.asm.org/content/aac/58/8/4885.full.pdf CQ and HCQ are well known drugs. And their use to combat previous corona viruses is not new or experimental. It has mainly just been "re-discovered".
-
Assume this is the study that is referenced: https://www.medrxiv.org/content/10.1101/2020.04.07.20056424v1.full.pdf From the study: Eligible participants were allocated to receive orally or via nasogastric tube high dose CQ (600mg CQ twice daily for 10 days or total dose 12g); or low dose CQ (450mg for 5 days, twice daily only on the first day, or total dose 2.7g). In addition, all patients received ceftriaxone and azithromycin. Issue 1 - HCQ is the recommend drug compound, NOT CQ. CQ is known to have undesirable side effects. So they used the non-recommended compound in their study. Issue 2 - Ultra high dosage in a twice a day dose for 10 days. And apparently poor EKG monitoring. Further: The high dose CQ arm presented more QTc>500ms (25%), and a trend toward higher lethality (17%) than the lower dosage. So the finding was that the absolute reckless dosage created QTc issues - a known potential side effect. The low (recommended) dosage did not exhibit this issue. And still - they used CQ vs. the recommended HCQ. QTc is the interval of the sinus rhythm heartbest (P-QRST cycle). BTW, they seem to believe an interval over 500 ms is bad (half a second). Concern starts when this number is above 420 and this becomes a real issue if the number exceeds 450. This study was bad. And reckless. And did not reflect the recommend treatment methods.
-
Debated on sharing this. But here it is. This situation hit close and hard. It involves a former co-worker who I and many others admired . He was someone I was sponsoring and mentoring for the next level before our function was thrown to the winds last year (90% layoffs). After originally being part of that last year upper management realized he was still critically needed and he stayed on. But he was looking since that time since the writing was clearly on the wall. We talked on Friday, April 3rd. It was his last day at our old company. He had found a perfect position with a large international dynamic company but would be working in the local office - perfect for him. He was a bit worried about his husband, a manager for a grocery store. His husband was getting tested for COVID since he was exhibiting some symptoms. I found out yesterday he had a sudden and massive heart attack and passed last Friday (10th) at home, with his spouse - who was quarantined since the COVID test had come back positive. There is no point here to be made and not looking for any sympathy. It does show that this overall situation is terrible. It is terrible for all of us. Its terrible for company executives, managers, workers, political leaders at all levels and everyone. No one has answers at their finger tips and there are risks with all decisions at this point. The perfect solution does not exist and there will likely be losses of someone close for most of us before this overall situation is done. So be nice to each over and do take care all.
-
"GRAB AND MOVE!" - John Pinette
-
The worldometer numbers now have more columns and are sortable by those columns. So you can look at things much easier. United States Coronavirus: 587,815 Cases and 23,654 Deaths - Worldometer I looked at the 'Yesterday' tab this morning since the noise of weekend reporting should be cleared out. It shows much better numbers than last week. - NY was below 700 deaths. - No other states were over 200 (NJ, MI last week). - MI was closest to NY with 115 deaths. - Everyone else below 100. - The median (not the mean) was 7 - right were Kentucky is. Median is the value where half are more and half are less. So half the states had less than 6 or less deaths yesterday according to the numbers. - Eight states had no deaths reported. - In terms of deaths per 1M of population: NY - 513 (highest), Kentucky - 23, Tennessee - 16, Wyoming - 2 (lowest). - National average of deaths per million - 71. - Seven states and DC are above this national average. - 43 states are below this national average. - The median of deaths per million by state is 21. Thus half the states have deaths per million of 20 or less. Kentucky is a bit higher than this at 23.
-
COVID - "Certificate of Vaccine ID". Scary proposition.
-
Eyeballing the Worldometer site numbers from yesterday I think most states are tracking at a level or lower death rate (that is assuming that the numbers have some level of validity though there is evidence they are overstated in a lot of cases). Even using these numbers - NY is still in a category by itself with over 700 deaths. Most of that obviously is NYC area. NJ and Michigan are also in their own category being the only other states with more than 200 deaths in one day, while no other state had more than 100. The use of HCQ/Zinc and blood transfusions to offset the damage to the hemoglobin should improve percentage of recoveries and shorten hospital stays considerably. As I noted in other post UK Healthcare held steady at 10 inpatients last week. Not sure if those where the same 10 or if some were discharged and new cases were admitted. I would assume more the later is likely.
-
Through 7 episodes. Will likely finish up tonight or tomorrow night. Agree on the points on Ruth.
-
UK Healthcare numbers as of 5:30 Thursday: Total number of test - 2,538 Positive test - 99 Inpatients under treatment - 10 (same as earlier in the week)
-
It seems they are closing in on the destructive nature of the virus. It seems the virus impacts the blood's ability to exchange CO2 and O2. This is what the video above describes. An "academic paper" describing this scenario was released today. Link here: COVID-19: Attacks the 1-Beta Chain of Hemoglobin and Captures the Porphyrin to Inhibit Human Heme Metabolism This ties together a lot of what has been seen. Basically O2 starvation will shut down organs simultaneously. If you already have a compromised condition, O2 starvation only makes it worse - quickly. Intubation (ventilators) can not fix the situation, though it may help as a bridge. Older people usually already have lower O2 levels so this is why this would impact older people. It seems the key now to improvement is transfusions. I have seen where people who undergo transfusions to add healthy red cells to their system improve. So hopefully they sort this out quickly.
-
A category that Kentucky leads the nation in. We have more deaths per positive test case than another state in the country. Twice the national average.
-
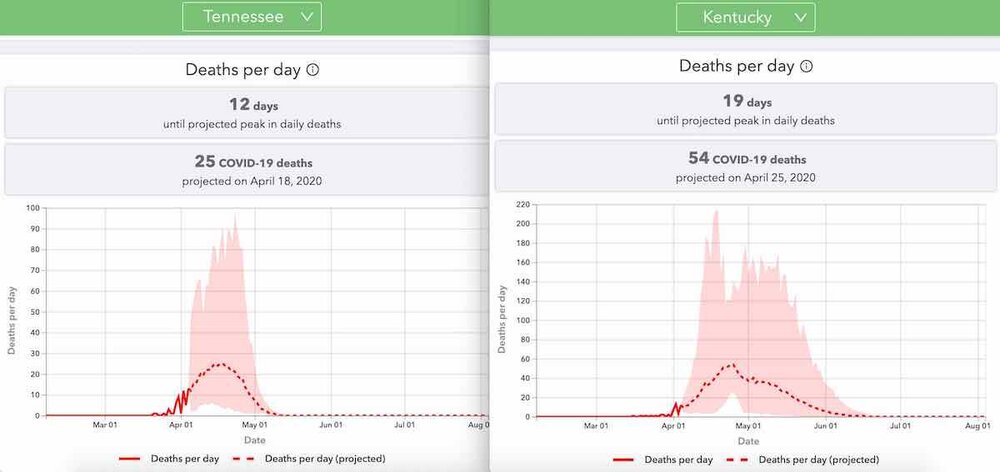
I keep trying to figure that out. Post #1252 in this thread was an attempt to figure it out by comparing states. I came away more confused than confirmed. NY (NYC area) is the epicenter of the worst situation. Is it a unique spot or is it the future? Let's hope its unique - and it likely is - or the ride is going to be bad medically to go with the economic catastrophe that is occurring and just getting started.One of three UK Health models has this going on till August.I do not see how they rationalize these numbers. Here is what has to happen to get to 47,000 deaths (over 1% of the population). Using 4,400,000 as our population count. 50% get infected. 2,200,000 (seems high) 10% need hospitalization. 220,000 (seems to be the base assumption) 20% of those hospitalized die. 44,000 (seems high, but is the number needed to get near their number) They are not real open with the math or assumptions of these models but reversing engineering back into the numbers can provide some insight. The UK Health models said August, mid-June and late May as of Friday.There is no vaccine for any other corona virus. Not sure why there is much hope that one will be found for this one. Unless its one that is advertised as effective but works like the flu vaccine that is hit and miss each year. There are very big money players in this game though, so something will likely come out. Herd immunity and HCQ/Zinc treatment are possibly the long term solution.Reports of farmers have to destroy crops or dump milk, etc. that was targeted for local restaurants.Was supposed to have a very expensive heart procedure the on the 17th. Cancelled. That's over $150,000 not billing - for one patient for one day. Multiply that by hundreds or more. This is bleeding the healthcare industry as bad as anybusiness. Dentists and Orthos are also getting killed by this.Side by side. Less peak, shorter period for Tennessee. No idea why. Tennessee's hot spots are Memphis and Nashville. Kentucky's somewhat hot spot is Louisville. This make sense since the more dense areas are having the most issues.





Account
Navigation
Search
Configure browser push notifications
Chrome (Android)
- Tap the lock icon next to the address bar.
- Tap Permissions → Notifications.
- Adjust your preference.
Chrome (Desktop)
- Click the padlock icon in the address bar.
- Select Site settings.
- Find Notifications and adjust your preference.
Safari (iOS 16.4+)
- Ensure the site is installed via Add to Home Screen.
- Open Settings App → Notifications.
- Find your app name and adjust your preference.
Safari (macOS)
- Go to Safari → Preferences.
- Click the Websites tab.
- Select Notifications in the sidebar.
- Find this website and adjust your preference.
Edge (Android)
- Tap the lock icon next to the address bar.
- Tap Permissions.
- Find Notifications and adjust your preference.
Edge (Desktop)
- Click the padlock icon in the address bar.
- Click Permissions for this site.
- Find Notifications and adjust your preference.
Firefox (Android)
- Go to Settings → Site permissions.
- Tap Notifications.
- Find this site in the list and adjust your preference.
Firefox (Desktop)
- Open Firefox Settings.
- Search for Notifications.
- Find this site in the list and adjust your preference.